found that there were 2,800 cases in 2024 and over 2,500 in 2025, with only a small fraction being tied to travel. Nearly all of the viral samples analyzed were descendants of the strain that sparked the 2022 outbreak. In short, once the virus arrived, it never went away.
"There's no set threshold for what constitutes endemicity of monkeypox virus (MPXV) in the United States," Ryan Standford, an epidemiologist in the Centers for Disease Control and Prevention's (CDC) Poxvirus and Rabies Branch and co-author of the report, told Live Science in an email. "But each year provides further evidence of this transition."
Why is mpox still spreading in the U.S., and what can be done to snuff it out? It's likely that too few people have received two doses of the mpox vaccine JYNNEOS, which together are 66% to 90% effective. But beyond low vaccination, there may be other, less-understood factors that are contributing to the continued spread, experts told Live Science.
"We don't quite know how it's able to persist at such low numbers across the entire country," said Joel Wertheim, a professor of medicine in the Division of Infectious Diseases and Global Public Health at the University of California, San Diego.
At the same time, public health efforts around mpox have dwindled. Without a sustained effort on that front, it's unlikely the disease will be eliminated from the U.S.
"We have vaccines, testing, and a much stronger understanding of the disease than we did in 2022," Dr. Demetre Daskalakis, chief medical officer of Callen-Lorde, a LGBTQ+ community health center in New York City, told Live Science in an email. "Our focus now should be making sure those tools remain accessible, especially for communities that continue to face ongoing risk," said Daskalakis, who coordinated the nation's mpox response during the previous presidential administration.
In the U.S., mpox is predominantly affecting men who have sex with men, and current vaccine recommendations are aimed at this group and their sexual partners. Mpox mostly spreads from person to person through close contact, and transmission during sex is playing a major role in the ongoing spread in the U.S.
Men who have sex with men are not more prone to mpox infection than anyone else. Rather, this transmission pattern stems from the outbreak beginning within a specific sexual network and then continuing to persist within the same network. "The mpox virus rediscovered the same transmission network that HIV had explored decades earlier," Wertheim said.
Wertheim noted that he's not surprised that mpox has remained largely confined to the same network, rather than leaping into new groups.
"From an evolutionary, ecological perspective, it's not hugely successful," Wertheim said. "It's sort of barely hanging on as an STI."
So if mpox is not hugely successful and we have a vaccine, how has the virus continued to circulate? One big factor is that too few at-risk people have been vaccinated, experts said.
To prevent an outbreak bigger than the one in 2022, between 21% and 35% would have to have immunity through vaccination or a past infection. If over 50% of the group had immunity, that would mean there's a "very small probability" of sustained local transmission, the CDC's modeling suggested.
The current case counts suggest we haven't hit the 50% mark, or a total of roughly 1 million complete vaccinations or past infections.
Data from the August report on mpox seems to support the idea that too few people are vaccinated. That said, information about vaccination status was missing for about 62% of the reported cases. Among the remaining cases, 76% were unvaccinated, while 10% had gotten one dose and 14% had gotten two.
In a subset of 860 cases, the effect of vaccination was striking: Unvaccinated people had nearly 10 times higher odds of hospitalization due to mpox than fully vaccinated people did.
It's difficult to pin down exactly how many at-risk people are vaccinated, given that that data is no longer tracked at the national level. "My understanding is that there's no mandatory reporting on mpox vaccination data," Wertheim said.
The CDC previously monitored national vaccination trends, comparing the number of people vaccinated to the overall at-risk population. But that tracking stopped in early 2024, when about 23% of the at-risk population had been fully vaccinated.
Meanwhile, "as the emergency phase faded from public attention, awareness and risk perception may have declined," Daskalakis said. Public health messaging about the virus and vaccination has also waned.
"In recent weeks, HHS [the Department of Health and Human Services] has pulled down some of the plain-language guidance, which is not helpful in supporting messaging," Daskalakis noted. This decision to remove online resources about mpox reflects the federal government's current stance against addressing issues that affect LGBTQ+ health, he told Live Science.
Although JYNNEOS substantially lowers the risk of severe mpox infection, the vaccine is not perfect, said Rachel Roper, a professor of microbiology and immunology at East Carolina University.
The virus typically enters the body through broken skin, the respiratory tract or mucous membranes (thin tissues found in the eyes, nose, mouth, anus and genitals). The mpox vaccine is good at generating systemic immunity, but it's not as good at guarding against the virus's immediate effects at those mucous membranes, said Roper, who studies poxviruses and vaccines against them.
Because mpox is largely spreading through sexual contact that involves those membranes, that slight gap in protection may also help to explain some of the ongoing spread, she suggested.
Given that mpox is already well established within some sexual networks in the U.S., "preventing endemicity entirely may be increasingly difficult," Standford told Live Science.
And notably, some federal funding cuts could undermine efforts to address mpox, Daskalakis said. These include cuts to Medicaid, mental-health services, housing programs, and HIV services such as the Ryan White HIV/AIDS Program.
Thankfully, looking at current mpox trends, "there's no indication we're returning back to 2022 levels," Wertheim told Live Science. So far in 2026, just under 1,000 mpox cases have been reported, according to the CDC. Month over month, the number of cases is generally trending downward. So, at a glance, the current situation seems better than it was in 2025, he said.
"We sort of seem to be on this razor's edge between endemicity and extinction," he said. "And it's not really clear which way it'll go."
Tipping the virus toward extinction will require healthcare providers to be informed and equipped to spot and manage cases, Daskalakis said. And communicating the importance of vaccination is key.
"One lesson from 2022 was that trusted messengers matter," he said. "We [at Callen-Lorde] work closely with LGBTQ+ communities and make information and vaccination opportunities available in settings where people already receive care." The clinic integrates conversations about mpox vaccination into routine health visits, sexual health services, HIV prevention programs and community outreach activities.
Tipping mpox toward extinction will also require enough investment to maintain the disease surveillance, vaccination, testing and treatment capacity that the federal government helped to expand in 2022, Daskalakis said. The vaccine itself is now commercially available to clinics and in adequate supply, he emphasized.
"The fact that we're seeing ongoing circulation underscores the need for sustained prevention efforts rather than viewing mpox as a resolved public health issue," he said. "Infectious diseases don't disappear simply because public attention shifts."
This article is for informational purposes only and is not meant to offer medical advice.
'> 'Mpox has not disappeared': Why the infectious disease is still spreading in the US and may be here to stay
Today, many countries affected by that outbreak — including Germany, Portugal and the United States — are still contending with local mpox transmission. Here's what to know about the virus, how it spreads and how to prevent infection.
What to know about mpox in the U.S.
Mpox is still spreading at low levels in the United States and may soon be considered endemic to the country. While case counts have fallen dramatically since the peak of the global outbreak in summer 2022, some people are still advised to get vaccinated against the virus.
Who should get vaccinated for mpox?
The mpox vaccine currently used in the U.S. is called JYNNEOS. One dose is about 35% to 86% effective, while the complete two-dose series is 66% to 90% effective. (The effectiveness varies, in part, because some studies include people with HIV and people without HIV, and inadequately treated HIV can undermine the body's response to vaccines.)
The JYNNEOS vaccine is not currently recommended for routine use in the general population because, beyond vulnerable groups, the risk is not high enough to warrant a universal vaccination strategy. The current outbreak is primarily affecting men who have sex with men, and those sexual networks are the primary targets for JYNNEOS vaccination.
However, not all men who have sex with men need to be vaccinated, according to the Centers for Disease Control and Prevention (CDC). Instead, vaccination is recommended for a specific subset of the group, including those who, in the last six months, have had more than one sex partner, have had sex at commercial sex venues, or have been diagnosed with other sexually transmitted diseases.
Nonbinary and transgender people with these risk factors are also recommended to get two doses of JYNNEOS, as are any sexual partners of anyone in the above groups.
Vaccines are also recommended after a suspected exposure to mpox, as they can help prevent or reduce the severity of the infection.
"For those who are eligible and have not yet completed vaccination, now is a good time to talk with a healthcare provider about getting protected," Dr. Demetre Daskalakis, chief medical officer of Callen-Lorde, an LGBTQ+ community health center in New York City, told Live Science in an email.
With the exception of laboratory researchers who work with mpox, people who have received two doses of JYNNEOS are fully vaccinated and do not need a booster, he said. And if a person has caught mpox in the past and recovered, they do not need to get a vaccine, he added.
Individuals who are recommended to get vaccinated against mpox should get two doses of the JYNNEOS vaccine. (Image credit: PATRICK T. FALLON/AFP via Getty Images)About the virus
The poxvirus family also includes smallpox, which has been eradicated worldwide. Mpox and smallpox cause some similar symptoms, but mpox tends to be far milder than smallpox. However, the viruses are closely related enough that vaccines designed to prevent smallpox can also protect against mpox.
Mpox was initially named monkeypox because the virus behind the disease was discovered in captive monkeys in Denmark. But monkeys are not the main hosts of the virus in the wild; rodents and small mammals mostly found in West and Central Africa likely are. Health officials changed the name to mpox in 2022.
There are two major branches of the mpox family tree, called clade I and clade II. These clades were historically thought to have very different death rates, with clade I being the deadlier of the two. The case-fatality rate (CFR) of clade I has been estimated to range from 1.4% to over 10%, depending on the outbreak, while the CFR for clade II has been estimated at between 0.1% and 3.6%.
However, as both clades have spread beyond Africa, data suggests that the CFR for clade I may be lower than once thought, said Joel Wertheim, a professor of medicine in the Division of Infectious Diseases and Global Public Health at the University of California, San Diego.
The features of a given outbreak — such as the surrounding health infrastructure, patients' access to timely medical care, and the population's underlying risk factors for severe disease — likely play a big role in determining the virus's death toll, Wertheim told Live Science. In short, rather than being an immutable feature of the virus itself, the CFR is dependent on the underlying health of and resources available to a given population.
How mpox spreads
Mpox can spread from infected animals to humans through the animals' bites or scratches. Additionally, people can get the virus when they come into close contact with animals and/or their bodily fluids during hunting, skinning, trapping, cooking, eating animals or handling carcasses, the World Health Organization (WHO) notes.
The virus also spreads from person to person, primarily through very close contact, including intimate contact during sex. The virus typically enters the body through broken skin, the respiratory tract or mucous membranes (thin tissues found in the eyes, nose, mouth, anus and genitals), spreading via bodily fluids such as spit, mucus or blood. People can also pick up the virus via objects, such as clothing or linen, that are contaminated with the bodily fluids of an infected person.
The virus can spread through small respiratory droplets expelled during speaking or breathing. However, this is thought to be a less-common transmission route than close contact. There is also evidence that asymptomatic spread sometimes occurs, though it's unclear how frequently that happens.
Mpox can spread from mother to baby during pregnancy or birth. This route of infection can result in pregnancy loss, stillbirth, death of the newborn, or complications for the mother.
Symptoms of mpox
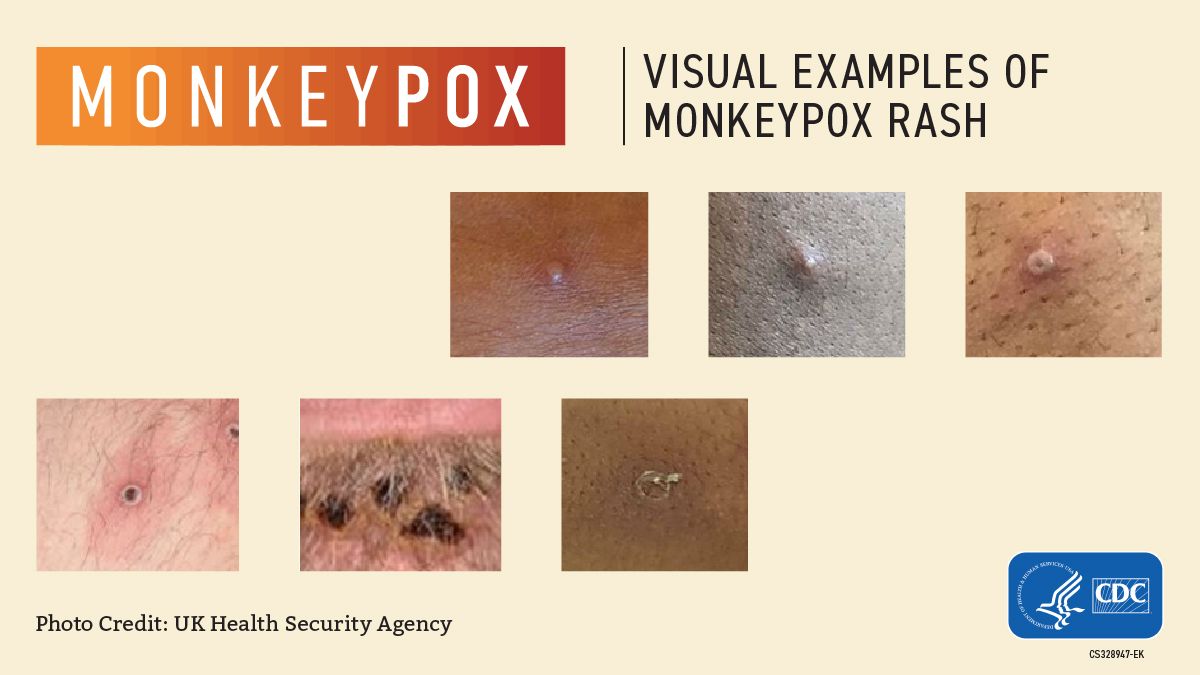 Centers for Disease Control and Prevention, National Center for Emerging and Zoonotic Infectious Diseases (NCEZID), Division of High-Consequence Pathogens and Pathology (DHCPP)
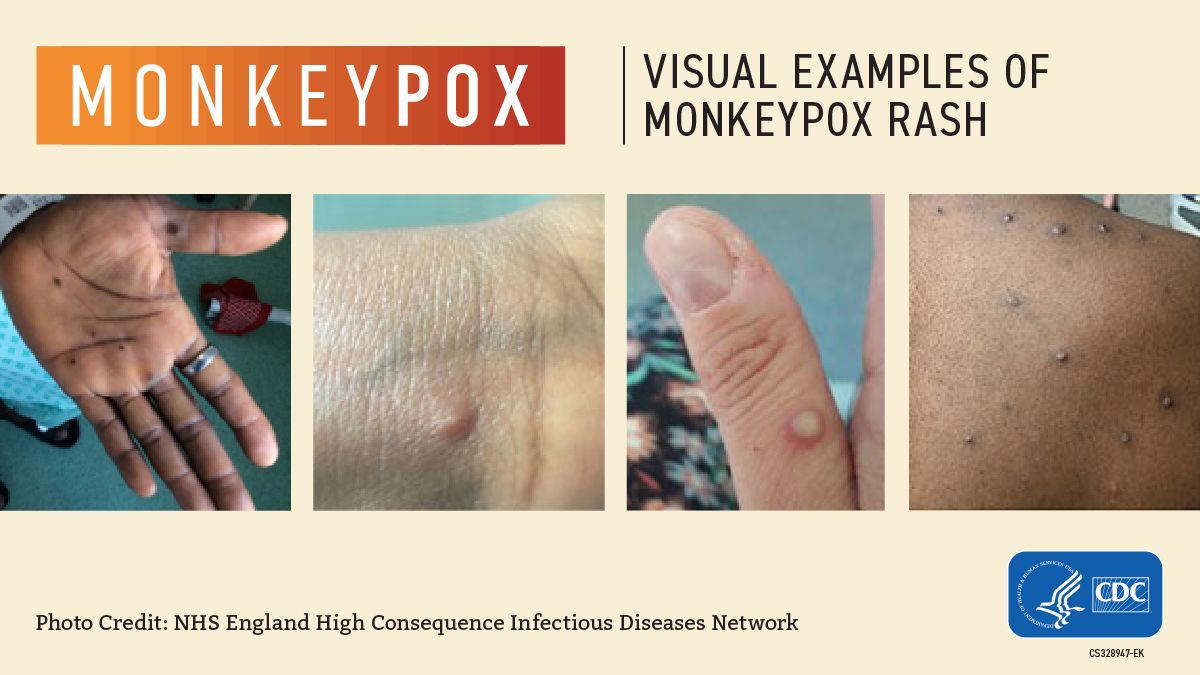 Centers for Disease Control and Prevention, National Center for Emerging and Zoonotic Infectious Diseases (NCEZID), Division of High-Consequence Pathogens and Pathology (DHCPP)
Symptoms of mpox typically appear within a week of a person being exposed to the virus, but they can sometimes take up to 21 days to develop. Once they emerge, symptoms last about two to four weeks, although the illness can linger longer in people with weakened immune systems.
Common symptoms include rash (see images), fever, sore throat, headache, muscle aches, back pain, swollen lymph nodes and low energy. Often, mpox rashes first appear on the face and then spread to other parts of the body; however, if a person becomes infected during sex, the rash may instead start around their genitals. The rashes begin as flat, discolored patches of skin and then progress into raised bumps, blisters, and large, pus-filled pimples that eventually scab over and fall off.
Some people with mpox develop painful swelling of the rectum (proctitis), while others have pain and difficulty when peeing (dysuria) or when swallowing.
Mpox rashes can make people vulnerable to bacterial skin infections, which can cause abscesses or other serious skin damage. Additional complications of the illness include pneumonia, infection of the cornea that can cause vision loss, and vomiting and diarrhea that causes dehydration or malnutrition. Mpox can also lead to blood infections, the intense immune reaction sepsis and, rarely, brain infections (encephalitis) or heart inflammation (myocarditis).
Children, pregnant people, and people with weakened immune systems, including from HIV infection, have a higher risk of serious illness and death from mpox.
Mpox prevention measures
Beyond vaccination, other strategies to decrease the risk of mpox infection include washing hands frequently, avoiding contact with contaminated objects and materials used by people with mpox, avoiding contact with other people's scabs or rashes, and using condoms, although they may only reduce, not eliminate, the risk of mpox exposure during sex.
Mpox treatment
Mpox treatment aims to manage a person's rashes and pain while also preventing complications. "Early and supportive care is important to help manage symptoms and avoid further problems," according to the WHO.
There is no antiviral drug approved for use in mpox, although some are available for emergency use in various countries. For example, the U.S. allows the use of certain smallpox medicines for mpox.
Severe mpox infections also may be treated with vaccinia immune globulin intravenous, which contains antibodies taken from the blood of people who were immunized against smallpox.
People who have recently been exposed to mpox can be given an mpox vaccine to reduce the severity of their symptoms or to prevent the illness altogether. This approach is known as post-exposure prophylaxis, or PEP.
"Post-exposure vaccine should be given as soon as possible, ideally within 4 days of exposure; administration 4 through 14 days after exposure may still provide some protection against monkeypox," the CDC states.
'> Mpox is still spreading in the US — here's what to know about vaccines, symptoms and treatment "This year's ozone hole shouldn't be a cause for alarm," Hannah Kessenich, a postdoctoral physicist at the University of Otago in New Zealand who predicted the 2026 ozone hole's extent using satellite data and a computer model, told Live Science in an email. "However, there are still many unanswered questions. It's something we need to keep a close eye on."
Accurate predictions
The latest figures from the Copernicus Atmosphere Monitoring Service indicate that the size of Antarctica's ozone hole has dropped to around 9.3 million square miles (24 million square km) since Sept. 20, making it unlikely that this year will break the 2015 record. However, scientists think the hole will remain large and fluctuate over the next few weeks, Kessenich said.
Antarctica's 2026 ozone hole peaked Sept. 20 and has been shrinking since. (Image credit: Copernicus Atmosphere Monitoring Service)Antarctica's ozone hole expands every year during the Southern Hemisphere's winter and spring. It typically reaches its maximum size between mid-September and early October, when temperatures are still freezing in the stratosphere and sunlight illuminates the frozen continent for the first time after months of darkness. The hole then shrinks again until late January as surrounding ozone-rich air mixes into the depleted region.
Antarctica's ozone hole was caused by emissions of ozone-destroying chlorofluorocarbons (CFCs) between the 1930s and late 1980s. These chemicals increased concentrations of chlorine in the stratosphere, thereby promoting a reaction that depletes the ozone layer. While countries signed the Montreal Protocol to phase out CFC use beginning in 1989, major CFCs have atmospheric lifetimes of 50 to 100 years, so the hole's recovery could take six decades, researchers estimate.
The ozone layer is particularly vulnerable above Antarctica due to the frigid conditions in the polar stratosphere. Temperatures below minus 108 degrees Fahrenheit (minus 78 degrees Celsius) trigger the formation of high-altitude clouds, whose icy surfaces turn inactive chlorine into its ozone-destroying form in the presence of sunlight. These conditions don't exist to the same extent in the Arctic, because warmer air from the midlatitudes mixes more readily with cold Arctic air than with Antarctic air, thereby blocking the formation of high-altitude clouds.
Changes in the polar vortex
This year's large ozone hole is caused by a very strong polar vortex, a wall of wind that encircles Antarctica and the Southern Ocean in the winter, trapping cold air above the continent. The polar vortex created colder-than-usual conditions in the stratosphere over Antarctica, accelerating the growth of the ozone hole.
We have to look at the longer term trends, and those metrics continue to tell us that the ozone hole is slowly recovering as expected.
Susan Solomon, professor of chemistry and environmental studies at MIT
Researchers haven't detected an increase in reactive chlorine, but the colder polar vortex has triggered more ozone depletion than usual, said Susan Solomon, a professor of chemistry and environmental studies at MIT who pioneered the study of Antarctica's ozone hole in the 1980s.
This size of this year's ozone hole is most likely a product of natural variability in atmospheric dynamics, Kessenich said.
"We expect ups and downs in the size of the hole from year to year," Solomon told Live Science in an email. "A year or a few years of bigger or smaller holes doesn't tell us anything about ozone loss or recovery; it is just variability. We have to look at the longer term trends, and those metrics continue to tell us that the ozone hole is slowly recovering as expected."
It's also reassuring that the ozone hole, while large, isn't as "thin" as in years past. The hole's extent is calculated based on the area above the continent with ozone values below 220 Dobson units, a measure of how many ozone molecules occur in a vertical column through Earth's atmosphere. Although the area of this year's ozone hole is huge, ozone values haven't dropped as low as in previous big-ozone-hole years, suggesting that there is less ozone "missing" from the hole compared with those years, Kessenich and her colleagues wrote in The Conversation.
But there's also the possibility that we've shifted to a new long-term trend of big ozone holes persisting until late spring, Kessenich said. Changes in global atmospheric dynamics unrelated to CFCs could be making longer-lived holes more likely, she and her colleagues wrote in the article.
There is also some evidence that climate change will strengthen the Antarctic polar vortex over time, which could lead to colder temperatures in the stratosphere and greater ozone losses in the spring, Kessenich said. If this year's polar vortex stays robust, the ozone hole could remain large well into November, she noted.
"It's too soon to tell what has been driving dynamical variability in recent years, but more research is needed," she added.
Help us improve Live Science Pro: We're always trying to make our content better. Leave us feedback about Pro here.
'> The ozone layer was supposed to be healing. So why is this year's Antarctic ozone hole so big?